
What are braces, and which option suits whom?
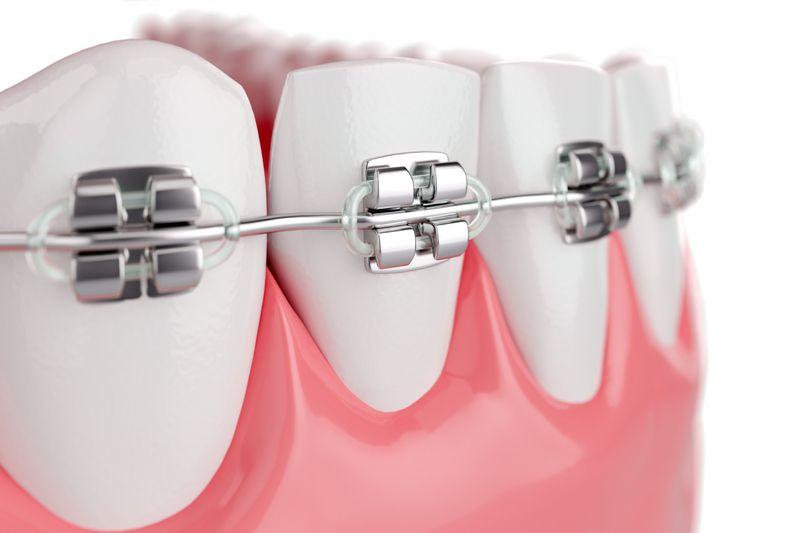
Braces (fixed orthodontic treatment) move teeth into a new position over time. Small brackets are glued to the teeth and a wire runs through them. They are used for crooked teeth, gaps between teeth and a bite where the upper and lower teeth do not meet properly. The brackets can be metal or tooth-coloured (ceramic), or fitted to the back of the teeth (lingual braces). The other option is clear aligners, which you take out and put back in yourself.
Which one suits you depends on how complex your case is and, for aligners, whether you can wear them consistently. In cases where teeth have to be taken out to make room, fixed braces have shown better treatment quality than clear aligners. In cases without extractions, no clear difference has been seen1 between the two. When treatment ends, a retainer helps keep the teeth in place.
This page is written for readers who live outside Turkey and are considering treatment at our clinic in Antalya, Turkey. On this page, "we" means that clinic.
- The choice depends on how complex your case is and whether you can wear aligners consistently. Where teeth need to be taken out, fixed braces have shown better treatment quality.
- When braces are fitted or adjusted, teeth can be tender for a few days; pain is usually at its worst in the first days.
- White spots (early decay) are common on teeth while fixed braces are on; careful brushing and cutting down on sugar are recommended.
- Fixed braces need adjustment appointments for months; if you live abroad, agree before treatment starts who will carry them out.
- When treatment ends, a retainer is used; your treating dentist decides how long you wear it.
Who is it considered for, and when is something else discussed first?
When braces may be considered
- Teeth that are crooked because there is not enough room for them in the jaw.
- Gaps between teeth.
- Lower teeth that close in front of the upper teeth, a crossbite, or front teeth that do not touch when the mouth is closed.
- Upper front teeth that sit well in front of the lower teeth (increased overjet). This is not only about appearance. In observational studies, children with an overjet over 5 mm had 1.81 to 2.43 times the odds2 of injuring their front teeth, by age group. This is an odds ratio; it does not mean twice as many injuries.
Orthodontic treatment is not only for children; it is also done in adults.
Early treatment in children
Some children's upper front teeth stick out noticeably. In these children, early treatment with a functional appliance, started between the ages of 7 and 11, reduced new injuries to the front teeth. In a Cochrane review, about 30 in every 100 children who waited until adolescence reported a new injury. In the early-treatment group, it was about 19 in 1003. This comparison included 332 children, and the quality of the evidence was moderate.
According to the same review, early treatment of prominent upper front teeth has not been shown to have any other advantage. Once both groups had finished treatment, the final overjet and the way the jaws related to each other did not differ meaningfully. Early treatment is a two-phase approach: after the first phase in childhood, a second course of treatment may still be needed later.
A long-lasting thumb-sucking or dummy (pacifier) habit is linked to bite problems, and the risk rises the longer it goes on4. But it is not the only cause; genetics, injuries and losing teeth early or late can also play a part5. We cannot give a specific age for a first orthodontic assessment on this page. Ask your dentist about your child's bite at dental check-ups; general information about children is on the children's dentistry page.
When something else is discussed first
- Decay or gum disease. The state of your teeth and gums is assessed at an examination before treatment. If there is decay or gum disease, how it will be dealt with before orthodontic treatment starts is discussed. This page does not explain how orthodontic treatment is planned for adults with gum disease. General information is on the gum disease page.
- When the problem lies in the position of the jaw bones. In adolescents, functional appliances reduced overjet by about 4.62 to 5.46 mm compared with no treatment3. These results come from small studies, and the quality of the evidence is low. There is no source showing that these appliances guide jaw growth in adults. In people who have stopped growing, adding jaw surgery to orthodontic treatment may be discussed for some jaw mismatches. We cannot say on this page when this is needed; your treating dentist explains the options after the examination.
- Only a small gap, or a shape problem in a single tooth. Sometimes a shorter route, such as adding composite to the tooth (composite bonding), can also be discussed.
Options: how do the appliances differ?
- Not having treatment. If crowding or a gap is only about appearance, not having treatment is also an option. A marked overjet, however, especially in children, is linked to a higher chance of injuring the front teeth (above).
- Fixed braces with metal brackets. The brackets are glued to the front surface of the teeth and stay in the mouth throughout treatment; you cannot take them out.
- Ceramic (tooth-coloured) brackets. They work in the same way as metal brackets and are less noticeable. Two clinical studies compared how often ceramic and metal brackets failed in the first year. One found more failures with ceramic brackets6, the other more with metal ones7. A review concluded that ceramic brackets may lead to more enamel fractures, particularly when they are removed8. Much of that evidence is from the laboratory, and no rate is known. In a 1990 laboratory test, ceramic brackets wore away more enamel than metal brackets from the teeth they rubbed against9. The test had no patients and gives no rate. Ask your treating dentist whether ceramic brackets suit your bite.
- Lingual braces. The brackets are glued to the back surface of the teeth and cannot be seen from outside. With lingual braces, tongue soreness has been reported clearly more often than with braces on the front of the teeth. Cheek and lip soreness has been reported less often. One review10 and another review published after it11 both reached this conclusion. The earlier review found no meaningful difference in overall pain10 in the first months. The later one concluded that people with lingual braces have more pain11, mostly because of tongue soreness. Changes in speech are much more common10 with lingual braces.
- Clear aligners. Clear trays that you take out and put back in yourself, replaced one after another. One review pooled 11 studies in adults (887 patients). Three studies in that review scored how the teeth were lined up and how they met at the end of treatment. In those, the result with aligners was weaker than with fixed braces12; the quality of the evidence is moderate. A newer review of 15 studies found better results with fixed braces in cases where teeth had to be taken out. In cases without extractions, no clear difference was found1. For mild to moderate crowding, treatment time was found to be similar13 with the two methods; the certainty of this evidence is low. More detail is on the clear aligner treatment page.
- Closing a gap at home with elastic bands is not an option. In one published case, an elastic band used by an 8-year-old child slipped under the gum. More than 75 per cent of the bone holding the teeth was lost, and two front teeth could not be saved14. This is a single case, not a rate.
| Metal or ceramic brackets | Lingual braces | Clear aligners | |
|---|---|---|---|
| Where does it go? | On the front of the teeth | On the back of the teeth | Fits over the teeth |
| Can you take it out? | No | No | Yes |
| Can it be seen from outside? | Yes; less so with ceramic | No | A little |
| When you eat | Stays in | Stays in | Taken out |
How does braces treatment go?
How long treatment takes depends on the state of your teeth, how severe the problem is and which appliance is chosen. According to the patient information page of the American Dental Association (ADA), most people are in treatment for one to three years5. This range comes from general patient information, not from research. Throughout that time, fixed braces need adjustment appointments at set intervals. Your treating dentist tells you the likely length of your treatment and how often you will need appointments after the examination.
On this page, "your treating dentist" means the dentist who plans and supervises your braces. Whether that dentist is an orthodontist is a question to ask (see who carries out the treatment, below).
Examination and records
Your teeth, gums and bite are examined. Photographs and impressions or a digital scan are taken; any X-rays needed are requested based on the examination findings.
Treatment plan
Which appliance suits you, whether any teeth need to be taken out and the likely length of treatment are discussed. If there is decay or a gum problem, how it will be dealt with before treatment starts is planned too.
Fitting the brackets
The tooth surfaces are prepared, the brackets are glued to the teeth and the wire is threaded through the brackets. With lingual braces, the brackets are glued to the back surface of the teeth.
Adjustment appointments
At set intervals the wires are changed or adjusted; sometimes elastics are used too. These appointments continue for the whole of treatment. Teeth can be tender for a few days after an adjustment.
Removing the brackets
When the teeth have reached their planned position, the brackets are taken off and the tooth surfaces are cleaned.
Retention
A fixed or removable retainer is made to keep the teeth in their new position. Your treating dentist tells you how long to wear it.

Risks and benefits
Risks and disadvantages
- Pain and tenderness. When braces are first fitted or adjusted, your teeth can feel tender and under pressure for a few days. In studies of the first week, pain was usually at its highest in the first 24 to 48 hours and eased within about a week15.
- White spots (early decay). While fixed braces are on, plaque builds up around the brackets. A review of white spots in orthodontic patients pooled 44 studies on new spots: they developed during treatment in about 34 in every 100 patients16. The same review reported that about 55 in every 100 orthodontic patients had white spots, counting all spots found, not only new ones. In people who had not had treatment, the figure was about 29 in every 10016. These two figures come from different groups of studies. The longer treatment lasted, the more common the spots were. These figures come from published studies, not from our own records, and they are not a personal risk estimate. This is why careful brushing and cutting down on sugary food and drinks are recommended.
- Teeth shifting after treatment. After orthodontic treatment ends, teeth tend to move back17 towards where they started. This is why the retention phase is part of treatment (below).
- Tongue soreness and speech changes with lingual braces. These side effects are described above, in the options section.
- Gum recession. Orthodontic treatment, poor oral hygiene and thin gums are listed among the factors that may raise18 the risk of the gums pulling back. This is an expert opinion and does not give a rate. Where the gum shows no disease, the same paper considers monitoring the area the appropriate approach.
- Loose brackets and poking wires. A bracket can come away from the tooth, or the end of a wire can poke into your cheek. If this happens, contact your treating dentist.
- Long treatment and regular check-ups. Treatment takes months, often years, and needs you to come to adjustment appointments regularly.
- A front tooth that was knocked in the past. Before braces are fitted, tell your treating dentist if a front tooth has ever been knocked or damaged. Such a tooth may need further treatment while wearing braces19.
- Other possible side effects. Other side effects, such as shortening of the tooth roots during treatment (root resorption), can also happen. We cannot say on this page how often they happen; ask your dentist at the examination.
Benefits
- The aim is to line the teeth up more evenly, improve the bite and close gaps. How far this is achieved varies; your treating dentist explains what is realistic for you.
- In children whose upper front teeth stick out noticeably, early treatment reduced new injuries to the front teeth (above).
Daily life and care while wearing braces
If you have pain
- Over-the-counter painkillers reduced orthodontic pain compared with taking no medicine. This result comes from a Cochrane review covering 32 studies; the quality of the evidence is moderate20. When anti-inflammatory painkillers (NSAIDs, such as ibuprofen) were compared with paracetamol (acetaminophen), no clear difference was found; the quality of that comparison's evidence is low. Follow the instructions on the pack; if you are not sure, ask your pharmacist or doctor.
- Non-drug methods such as chewing gum, bite wafers and vibration devices have not been shown21 to reduce orthodontic pain. The evidence on this is of very low quality.
- In the first days, soft foods may be easier to chew.
Eating and drinking
- Avoiding chewing gum during fixed braces treatment is recommended; gum can stick to the braces19. It is also best to avoid hard, crunchy and sticky foods.
- Cut down on sugary food and drinks; sugar can lead to plaque building up5 around the brackets.
Cleaning
- Brush your teeth twice a day with fluoride toothpaste; take care around the brackets and along the gumline.
- Clean between the teeth and under the wires, not only where food gets caught. Ask your dentist which small brush or floss to use.
- Alongside your orthodontic check-ups, keep having regular check-ups with your dentist. How often you need them is set according to your risk of decay and gum disease22.
Speech
In a review that looked at all kinds of orthodontic appliances, most changes in speech cleared up within a few weeks23. A lisp on the 's' sound, however, could last more than 3 months. The evidence in this review is of low quality.
Is the result permanent? The retention phase
When treatment ends, teeth tend to move back towards where they started. A retainer is used to hold the teeth19 in their new position.
- Which retainer? There are fixed wires glued behind the teeth and removable retainers. A Cochrane review covering 47 studies has not shown any one of them to be clearly better17 at keeping teeth straight. Each has pros and cons in terms of breakages, comfort and the gums; the certainty of the evidence is low or very low.
- For how long? Your treating dentist decides how long you wear the retainer19. According to a UK opinion piece, the British Orthodontic Society (BOS) has given patients the message that retainers should be worn for life24. The author of the piece, a dentist, argues that research does not support this general advice. He notes that most retention studies lasted 6 to 24 months24. There is no evidence-based fixed length of time, and no retention method has been shown to hold teeth completely still for life.
- A fixed retainer wire can come loose. In studies, bond failure with multistrand twisted wires has been reported at between 12 and 50 per cent25. This is not a single rate but the lowest and highest values reported in different studies, not our own figures. The quality of the evidence is low.
- A gap between the front teeth can open again. A small retrospective study followed 30 patients whose gap between the two upper central incisors had been closed. On average 5 to 6 years after retention stopped, the gap had reopened in 6 in every 10 patients26. The reopening averaged 0.49 mm across the whole group and 0.78 mm in the patients whose gap reopened26. This rate does not apply to other gaps between teeth. Gaps between the central incisors and the teeth next to them (the lateral incisors) reopened less often.
Who carries out the treatment?
Treatment in Antalya is provided by our clinic.
Orthodontics is one of the nine dental specialties set by law in Turkey27. Ask who will plan your treatment, who will fit the braces and who will carry out the adjustments, and what their titles are. You can find our dentists' titles on the Our dentists page.
When should you contact your treating dentist or your dentist at home?
If any of these happens, contact your treating dentist or your dentist at home.
- Pain that lasts more than a few days19 after braces are fitted or adjusted
- A bracket that has come off a tooth, or the end of a wire poking into your cheek or tongue
- A fixed retainer wire that feels loose or has broken
- A removable retainer that no longer fits or has broken
- White spots around the brackets, or gums that bleed or are swollen
- A knock to the front teeth during or after treatment
If you think you have a dental abscess, do not wait; an abscess does not go away on its own and needs urgent dental treatment28. If you have swelling in your face or jaw, or a fever, get seen the same day by a dentist where you are.
Emergencies. The following need urgent medical help28. Do not wait for a dental appointment or for the clinic's reply. Go to the nearest emergency department or call the emergency number where you are (112 if you are in Turkey).
- Swelling that makes it hard to breathe, speak or swallow
- Swelling that spreads to the eye or the neck29
- Swelling or pain in the eye, or sudden problems with your sight
- A lot of swelling inside your mouth
- Difficulty opening your mouth
Before you fly home
Know who will carry out your next adjustment, where and when. Make sure you have written care instructions, your treatment record and a way to reach the clinic.
Once you are home
If a bracket comes off or a wire pokes, write to the clinic and send photographs. See the dentist or orthodontist who looks after your braces where you live. In the emergencies above, do not wait for a reply.
If you are coming from abroad
Braces are not a one-trip treatment. After the brackets are fitted, the wires are changed or adjusted at set intervals until treatment ends. So before you decide, the practical question is who will carry out those appointments.
Who carries out the adjustments?
There are two ways. You come back to Antalya for the adjustment appointments, or a dentist or orthodontist near your home takes over after the brackets are fitted. Repeated trips over many months need to fit your work, your family and your budget. A dentist or orthodontist at home has to agree to take over treatment in progress, and some may not want to. They may also want to change the plan or the appliance. Agree the arrangement before the brackets are fitted, and have it in writing. It should say who carries out the adjustments, roughly how often, and what happens if one is missed.
If you are considering clear aligners instead, ask the same question about their check-ups; see clear aligner treatment.
The examination comes first
The UK dental regulator, the GDC, states that some interactions between dentists and patients can be provided safely and effectively at a distance. For other stages of care, however, a face-to-face appointment or a physical examination is needed for patient safety. For orthodontics, the GDC says there is currently no effective substitute for a physical clinical examination30. This is the view of a UK regulator, not a binding rule in Turkey. Before you book, you receive a written preliminary plan based on the photographs and any X-rays you send. It sets out the appointments and how many days the first trip needs. It is not a diagnosis: the examination confirms or changes it, and with it the days and the cost. If it changes, you receive the revised plan in writing before treatment starts. You can take time to decide, and you can say no, or ask to stop, at any stage. Having braces with a dentist or orthodontist where you live remains an option.
Your dentist at home
Talk to your own dentist before you go. They need to know the plan, and you keep seeing them for check-ups during treatment (see daily care above). Ask for a written record: the appliance and brackets used, the stage your treatment has reached and the wires in place. Ask too for copies of your X-rays, scans and photographs, and for the aftercare plan in writing. A dentist or orthodontist at home needs it to continue treatment or repair the braces. In Turkey, the health tourism regulation entitles international patients to an itemised bill. On request, they also get free copies of the records of the materials used, the tests and the imaging31.
The retention phase also happens at home. A fixed retainer wire can come loose, and a removable retainer can break or stop fitting (see above). Agree who checks and repairs the retainer where you live.
Problems after you return are usually first seen by a dentist where you live. A dentist at home may not take over braces fitted abroad. Before you travel, ask the health service or your insurer in the country where you live what they would cover.
Flying. We have found no guidance that sets a waiting time before flying after braces are fitted or adjusted. A 2023 review of flying after dental treatment does give times for tooth extraction, which matters if teeth are taken out to make room. It suggests waiting 24 to 48 hours after a simple extraction and 72 hours after a surgical one32. These intervals assume no pain, swelling or bleeding at the treated site. The authors note that the research is limited and comes mainly from military aviation. The intervals are a starting point for the dentist's decision, not clearance to fly. Ask the clinic when you can fly after the brackets are fitted.
Questions to ask before you commit. Ask these before treatment abroad, and ask for the answers in writing:
- Who will carry out my treatment, and what are their qualifications?
- Are you regulated by a professional body and registered with it?
- Is the work guaranteed, are the terms in writing, and for how long do they apply?
- What aftercare do you provide, and who can I contact after the treatment?
- If there are complications, who pays for further treatment, extra flights and the hotel?
- Do you have a complaints system, and can I see a copy?
The full list of questions to ask before treatment abroad is on our page about dental treatment abroad.
What determines the cost?
This page does not show prices. A treatment plan is prepared for you after an examination. The main factors that shape it are:
- The appliance chosen: metal or ceramic brackets, lingual braces or clear aligners
- How severe the problem is and the likely length of treatment
- Extra procedures, such as taking teeth out, or fillings or gum treatment before orthodontic treatment
- The number of adjustment appointments, and how many of them are in Antalya
- The retainer after treatment and its check-ups
Ask for the plan in writing. It should say what is included, and especially whether the adjustments, the retainer and its check-ups are included. Ask too who pays for further treatment and extra travel if there is a complication.
Which appliance suits you?
Send photographs of your teeth and your smile, and any X-rays you have. Our dentists will write back with a first view on the likely options and how the appointments could work from where you live. It is not a diagnosis: the plan itself follows an examination in person.
Frequently Asked Questions
Braces or aligners?
The answer depends on how complex your case is and whether you can wear aligners consistently. In cases where teeth have to be taken out to make room, fixed braces have shown better treatment quality. In cases without extractions, no clear difference has been found between the two. Your treating dentist tells you which suits you after the examination.
How long does braces treatment take?
It depends on the state of your teeth, how severe the problem is and which appliance is chosen. General information is above, in the section on how treatment goes. Your treating dentist tells you the likely length of your treatment after the examination.
Do I need to come back to Antalya for adjustments?
Fixed braces need adjustment appointments at set intervals until treatment ends. They can be done in Antalya, which means repeated trips, or by a dentist or orthodontist near your home who agrees to take over. Agree which before the brackets are fitted, and have it in writing.
How many days do I need in Antalya to have braces fitted?
It depends on the examination, the records needed and whether other treatment, such as fillings or gum treatment, comes first. Your written plan states the appointments and the days before you book. The examination can change it.
Do braces hurt?
When braces are fitted and adjusted, your teeth can feel tender and under pressure for a few days. Pain is usually at its worst in the first days and then eases. Over-the-counter painkillers can help; if the pain lasts more than a few days, contact your treating dentist.
Do braces cause decay?
While braces are on, plaque builds up around the brackets and white spots (early decay) on the teeth are common. Careful brushing, fluoride toothpaste and cutting down on sugary food and drinks are recommended to lower this risk.
Can adults have braces?
Yes. Orthodontic treatment is not only for children. Before treatment, the state of your gums and teeth is assessed at an examination. If the problem lies in the position of the jaw bones, your treating dentist explains the options.
What if a bracket comes off after I have gone home?
Write to the clinic and send a photograph, and see the orthodontist or dentist who looks after your braces where you live. A loose bracket or wire is repaired at an appointment. If your face or jaw swells, see a dentist the same day. If you have trouble breathing or swallowing, go to the nearest emergency department or call the emergency number where you are.
Will my teeth move back after treatment?
Teeth tend to move back towards where they started. A retainer is used to reduce this, and your treating dentist decides how long you wear it. There is no evidence-based fixed length of time, and no method has been shown to hold teeth completely still. It is important to wear the retainer as advised and for as long as advised.

Dt. Dilek AKSU GÜLER
Dentist · Founder
She has completed advanced training in implantology and works in aesthetic restorations and smile design.
Sources
- Quality and stability of orthodontic treatment outcomes with clear aligners versus fixed appliances: a systematic review and meta-analysis. European Journal of Orthodontics 2025;47(6):cjaf091. 2025.↩doi.org
- The association of overjet size and traumatic dental injuries - a systematic review and meta-analysis. Dental Traumatology 2019;35(4-5):217-232. 2019.↩doi.org
- Orthodontic treatment for prominent upper front teeth (Class II malocclusion) in children and adolescents. Cochrane Database of Systematic Reviews 2018;3:CD003452. 2018.↩doi.org
- Establishing the association between nonnutritive sucking behavior and malocclusions: a systematic review and meta-analysis. Journal of the American Dental Association 2016;147(12):926-934.e6. 2016.↩doi.org
- Braces. American Dental Association, MouthHealthy.↩mouthhealthy.org
- Metallic vs Ceramic Bracket Failures After 12 Months of Treatment: A Prospective Clinical Trial. International Dental Journal 2024;74(6):1371-1377. 2024.↩doi.org
- A Clinical Comparison of Failure Rates of Metallic and Ceramic Brackets: A Twelve-Month Study. BioMed Research International 2020;2020:9725101. 2020.↩doi.org
- Structural and Color Alterations of Teeth following Orthodontic Debonding: A Systematic Review. Journal of Functional Biomaterials 2024;15(5):123. 2024.↩doi.org
- Enamel abrasion from ceramic orthodontic brackets under an artificial oral environment. American Journal of Orthodontics and Dentofacial Orthopedics 1990;98(2):103-109. 1990.↩doi.org
- Comparison of adverse effects between lingual and labial orthodontic treatment. The Angle Orthodontist 2013;83(6):1066-1073. 2013.↩doi.org
- Adverse effects of lingual and buccal orthodontic techniques: a systematic review and meta-analysis. American Journal of Orthodontics and Dentofacial Orthopedics 2016;149(6):820-829. 2016.↩doi.org
- Treatment outcome with orthodontic aligners and fixed appliances: a systematic review with meta-analyses. European Journal of Orthodontics 2020;42(3):331-343. 2020.↩doi.org
- Duration of orthodontic treatment with clear aligners versus fixed appliances in crowding cases: a systematic review. Clinical Oral Investigations 2024;28(5):249. 2024.↩doi.org
- The Risks of DIY Braces: An Orthodontic Case Study. American Association of Orthodontists. 2024.↩aaoinfo.org
- Comparison of pain intensity and impacts on oral health-related quality of life between orthodontic patients treated with clear aligners and fixed appliances: a systematic review and meta-analysis. BMC Oral Health 2023;23(1):920. 2023.↩doi.org
- Prevalence, incidence and risk factors of white spot lesions associated with orthodontic treatment - a systematic review and meta-analysis. Orthodontics & Craniofacial Research 2025;28(2):379-399. 2025.↩doi.org
- Retention procedures for stabilising tooth position after treatment with orthodontic braces. Cochrane Database of Systematic Reviews 2023;5:CD002283. 2023.↩doi.org
- Mucogingival conditions in the natural dentition: narrative review, case definitions, and diagnostic considerations. Journal of Clinical Periodontology 2018;45 Suppl 20:S190-S198. 2018.↩doi.org
- Braces. NHS (UK). 2026.↩nhs.uk
- Pharmacological interventions for pain relief during orthodontic treatment. Cochrane Database of Systematic Reviews 2017;11:CD003976. 2017.↩doi.org
- Non-pharmacological interventions for alleviating pain during orthodontic treatment. Cochrane Database of Systematic Reviews 2016;12:CD010263. 2016.↩doi.org
- Dental checks: intervals between oral health reviews (clinical guideline CG19). National Institute for Health and Care Excellence, published 27 October 2004. 2004.↩nice.org.uk
- Speech and orthodontic appliances: a systematic literature review. European Journal of Orthodontics 2018;40(1):29-36. 2018.↩doi.org
- British Orthodontic Society's initiative on orthodontic retention, a GDP's perspective. British Dental Journal 2018;224:481-486 (Mc Crory PV). 2018.↩nature.com
- Failure of fixed orthodontic retainers: a systematic review. Journal of Dentistry 2015;43(8):876-896. 2015.↩doi.org
- Stability of orthodontic midline diastema closure: 30 patients, mean 5.6 years after retention. Journal of Applied Oral Science 2014. 2014.↩pmc.ncbi.nlm.nih.gov
- 1219 sayılı Tababet ve Şuabatı San'atlarının Tarzı İcrasına Dair Kanun (consolidated text). T.B.M.M.; RG 14/4/1928 No 863; consolidated on mevzuat.gov.tr. 1928.↩mevzuat.gov.tr
- NHS: Dental abscess. NHS (nhs.uk). 2026.↩nhs.uk
- NHS: Toothache. NHS (nhs.uk). 2024.↩nhs.uk
- GDC statement on 'direct-to-consumer' orthodontic treatment. General Dental Council (UK).↩gdc-uk.org
- Uluslararasi Saglik Turizmi ve Turistin Sagligi Hakkinda Yonetmelik. T.C. Saglik Bakanligi, Resmi Gazete 26/4/2025, No 32882. 2025.↩resmigazete.gov.tr
- Dental tourism and the risk of barotrauma and barodontalgia (narrative review with guiding principles). British Dental Journal 2023;234(2):115-117. 2023.↩doi.org
