
What is root canal treatment, and when is it considered?
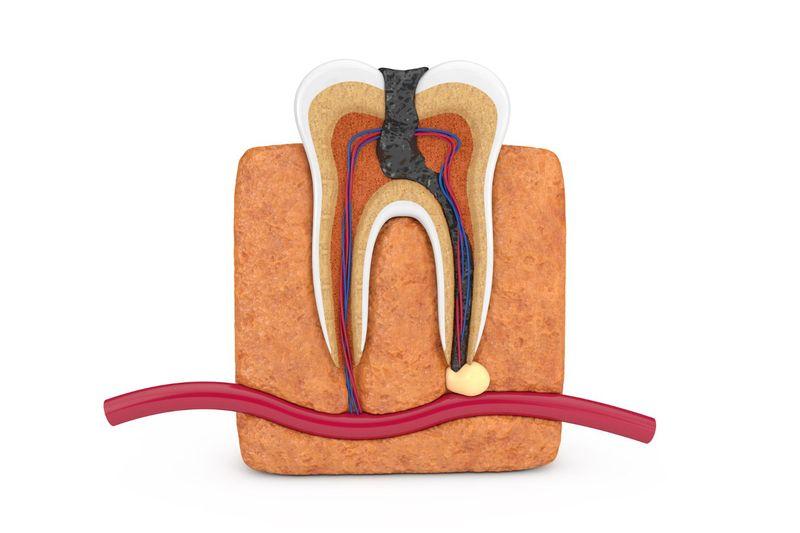
Root canal treatment removes the soft tissue inside a tooth (the pulp, often called the nerve) when it is inflamed beyond recovery or has died. The root canals are then cleaned and filled. The aim is to keep the tooth instead of taking it out.
It is done under local anaesthetic; it can be finished in one visit, but it often takes more than one. The alternative is to have the tooth extracted and then either replace it with an implant, a bridge or a denture, or leave the gap.
Over the long term, root-filled teeth and single crowns on implants have been found to stay in the mouth at similar rates1; very few studies have compared the two treatments directly. Which suits you depends on how much sound tooth is left and on the state of your gums and bone. This page is about permanent teeth; for baby teeth, see the children's dentistry page.
- Root canal treatment aims to keep a tooth whose nerve has become inflamed or has died, without extracting it.
- A dental abscess does not go away on its own; antibiotics alone do not replace root canal treatment or an extraction.
- Most root-filled teeth stay in place for years, but staying in place is not the same as being trouble-free.
- After treatment, the top of the tooth is restored permanently with a filling, an onlay or a crown.

Who needs it, and when is another option considered?
When root canal treatment may be needed
- When decay has reached the nerve of the tooth and the inflammation in the nerve has become irreversible. Pain that starts on its own, wakes you at night or lasts a long time can point to this; the diagnosis is made with an examination and an X-ray.
- When the nerve of the tooth has died. This can happen after a knock to the tooth, or under deep decay and large fillings. Sometimes it causes no symptoms at all and is picked up only when the examination, nerve tests and X-rays are assessed together.
- When there is an abscess, or inflammation at the tip of the root.
- The nerve can also lose its vitality over time in teeth that have had a crown. The pooled results of 37 studies cover teeth that were vital at the start and received a crown, a partial restoration or served as a bridge support. Of every 100 of these teeth, about 5 lost the vitality of their nerve2. The certainty of the evidence is low.
Before an examination, no one can say for certain that a tooth will need root canal treatment. According to the European guideline, in very deep decay the risk of exposing the nerve is high and this risk should be anticipated3. Whether the nerve needs treatment is sometimes clear only while the decay is being removed.
When another option is considered first
- Deep decay without symptoms. This covers teeth with no pain, or only brief sensitivity triggered by something hot, cold or sweet. For these teeth, the European guideline recommends selective or stepwise removal3, in which the soft part next to the nerve is left in place instead of all the decay being removed. This is a weak recommendation and the certainty of the evidence is very low.
- Teeth whose nerve is exposed while decay is removed, and which do not ache on their own. Removing only part of the nerve (pulpotomy) appears to be as effective as root canal treatment3; however, this rests on a single study and the certainty of the evidence is low. The guideline also recommends3 partial or full pulpotomy for some teeth with signs of irreversible inflammation of the nerve. This is a weak recommendation and the certainty of the evidence is low. These studies compared two types of pulpotomy with each other, not pulpotomy with root canal treatment. Whether it suits a particular tooth is decided by the examination findings and your dentist. The guideline notes that not every dentist may be able to carry out this procedure on adult teeth.
- Teeth that cannot be saved. If not enough sound tooth is left to restore, or the root has a fracture that cannot be repaired, root canal treatment will not save the tooth. In that case, extraction and what will replace the missing tooth are discussed.
- Antibiotics do not replace treatment. Antibiotics do not take the place of root canal treatment or an extraction; in some cases they may be needed in addition (see "Pain and abscess" below). Antibiotics are not recommended for the pain of an inflamed nerve; there is not enough evidence4 that they reduce it. The only trial on this included 40 people.
Options: keeping the tooth or having it out
- Doing nothing. A dental abscess does not go away on its own5 and needs treating by a dentist. If there is inflammation at the tip of a root that causes no symptoms, talk to your dentist about what to do.
- Root canal treatment. Your own tooth stays in the mouth and the neighbouring teeth are not touched. After treatment, the top of the tooth is restored with a filling, an onlay or a crown.
- Extraction and an implant. The tooth is taken out, an implant is placed in the jawbone in its place, and a crown is made on top. This is a surgical procedure, and there is a wait while the bone heals. In a review of 46 studies on single missing teeth, of every 100 implants, about 97 were still in the mouth after five years and about 95 after ten6. These rates are for the implant itself: in the same review, of every 100 crowns on top, about 96 were in use after five years and about 89 after ten6. Even among implants that stayed in the mouth, complications such as screw loosening, gum problems and bone loss were reported often6. Details are on the dental implant treatment page.
- Extraction and a bridge. The missing tooth is replaced with a bridge attached to the teeth on either side; for a conventional bridge, these teeth also have to be reduced.
- Extraction and a partial denture, or leaving the gap. A partial denture can be taken in and out. For some gaps at the back of the mouth, leaving the gap is also discussed; your dentist assesses how this would affect chewing.
In a review of 143 studies, root-filled teeth and single crowns on implants were found to stay in the mouth at similar rates1 over the long term. Studies comparing the two treatments directly are extremely rare. The studies also defined success so differently that their success rates could not be compared1. So it is not accurate to say either that "a natural tooth always lasts longer" or that "an implant always lasts longer".
| Root canal treatment | Extraction and an implant | Extraction and a bridge | Extraction, gap left | |
|---|---|---|---|---|
| Do you keep your own tooth? | Yes | No | No | No |
| Surgery | None | Extraction and implant placement | Extraction | Extraction |
| Are the neighbouring teeth reduced? | No | No | Yes, for a conventional bridge | No |
| What is needed afterwards | A filling, an onlay or a crown | A crown on the implant | A bridge | Nothing |
How is root canal treatment done?
The steps below are for a first root canal treatment on a permanent tooth. According to the UK's National Health Service (NHS), treatment usually takes 2 or more appointments; appointments can take 1 to 2 hours, sometimes longer7. This describes practice; we did not find a review that measured appointment length.
Between treatment completed in one visit and treatment spread over several, no clear difference in failure on X-rays at one year and beyond was found (13 studies, 1,505 teeth)8. This is not evidence that the two approaches are equivalent. Your dentist will tell you after the examination how many visits your tooth needs.
If you feel anxious about treatment, tell your dentist. You can read what sedation is and who it suits on the conscious sedation page.
Examination and X-ray
The state of the tooth and of the tip of the root is assessed with an examination and an X-ray. At this stage, it is decided whether the tooth can be restored and whether root canal treatment is suitable.
Local anaesthetic
The tooth and the area around it are numbed. If you feel pain during the procedure, say so; more anaesthetic can be given.
Isolating the tooth
A rubber sheet (rubber dam) is placed around the tooth. This keeps the tooth separate from saliva and dry.
Cleaning the canals
Inflamed or dead tissue is removed through a small opening made in the tooth. The root canals are cleaned and shaped with fine instruments and rinsed with a disinfecting solution. The length of the canals is measured and, if needed, checked with an X-ray.
Between visits
If treatment is spread over more than one visit, a medicine is placed in the canal and the tooth is closed with a temporary filling. While the temporary filling is in, do not chew hard food on that side.
Filling the canals
The cleaned canals are filled and sealed with a rubber-like material (gutta-percha) and a root canal sealer.
Permanent restoration of the tooth
The top of the tooth is restored with a filling, an onlay or a crown. If very little tooth is left, a post may be placed in the root canal to hold the restoration on top.
Review
Healing at the tip of the root is monitored with X-rays at intervals your dentist sets.
Risks and benefits
Risks and disadvantages
- Pain after treatment. Pain is common before root canal treatment and eases after it. In one review, the average share of people reporting pain was: 81 in every 100 before treatment, 40 after 24 hours and 11 after one week9. These rates were calculated from 30, 11 and 12 studies respectively. They are averages across studies, not the chance for any one patient.
- More pain in the first week after a single visit. After treatment completed in one visit, more people reported pain in the first week than after the first visit of treatment spread over several (5 studies, 638 teeth, moderate-certainty evidence8). In the first three days after the canals were filled, no difference in the intensity of pain was found (12 studies, 1,258 teeth, low-certainty evidence)8.
- Flare-up. Severe pain or swelling after treatment that needs an unplanned appointment is uncommon. It occurred in 688 of 24,320 cases in 15 studies, that is, in about 3 in every 100 cases10. It was reported more often in teeth that ached on their own, or hurt when tapped, before treatment. Each of these findings rests on 3 non-randomised studies, and the certainty of the evidence is low or very low.
- The tip of the root does not heal fully in every tooth. In a review combining studies published between 1922 and 2002, with at least one year of follow-up, the success rate measured as complete healing on X-rays was between 68 and 85 per cent11. For teeth that do not heal, repeat root canal treatment, surgery at the tip of the root or extraction is discussed. We do not give a source for the success rates of these options on this page; ask your dentist what can be expected for your tooth.
- The tooth can break. Decay, earlier fillings and the opening made for treatment may have reduced the sound tissue in the tooth, which raises the risk of it breaking. This is why the top of the tooth needs a permanent restoration.
- Discolouration. A tooth whose nerve has died can darken over time. Such a tooth can be lightened by bleaching from the inside; in rare cases this procedure has been linked to resorption of the root surface12. The source gives no rate for this side effect.
Benefits
- Your own tooth stays in the mouth; no extraction is needed and the neighbouring teeth are not touched.
- Most root-filled teeth stay in place for years (see "How long does it last?" below).
Pain and abscess: what to do until treatment
- Painkillers. Until you see a dentist, the option the guideline recommends is ibuprofen, if it is suitable for you, on its own or together with paracetamol. This evidence comes from studies of pain after tooth extraction, not directly from toothache, and its certainty is low13. Follow the instructions on the pack and do not exceed the recommended daily dose; if there is bleeding in the mouth, do not take aspirin or ibuprofen. This self-care advice is for 24 hours14; if the pain continues or you need more painkillers, talk to your pharmacist or dentist. If you are pregnant, take regular medication, or have a stomach, kidney or bleeding problem, talk to your pharmacist before choosing a painkiller.
- Do not put a tablet next to the tooth. Placing a painkiller next to the aching tooth or on the gum can damage the tissue14. Tablets are swallowed.
- Antibiotics do not replace root canal treatment. In adults having root canal treatment for inflammation at the tip of the root or an abscess, antibiotics added to the treatment have not been shown to reduce pain or swelling (3 trials, 134 people)15. The certainty of the evidence is low or very low. If the infection is spreading, if there are general symptoms such as a fever, or if the pus cannot be drained straight away, antibiotics may be needed16; your dentist decides.
- Do not squeeze an abscess at home. An abscess is treated by a dentist draining the pus under local anaesthetic and removing the cause5. If the cause is in the tooth, this usually means root canal treatment or having the tooth out.
After treatment, and daily care
The anaesthetic can take a few hours to wear off. Do not eat until the numbness has gone, and take care not to bite your cheek or tongue. According to the NHS, the area may feel swollen and sore after treatment, but this is expected to settle within a few weeks7.
Daily care
- Until the top of the tooth has been restored permanently, do not chew hard or sticky food on that side. The temporary filling may fall out or the tooth may break.
- Take painkillers as directed on the pack or as your dentist advises.
- Brush your teeth twice a day with a fluoride toothpaste; clean between your teeth every day with interdental brushes or floss.
- Do not put off the appointment for the permanent restoration.
How long does it last?
The honest answer to this question is a rate, not a number of years. The rates below describe the tooth staying in the mouth; they do not mean there were no problems during that time.
In the pooled results of a review of 14 studies, of every 100 root-filled teeth, about 86 were in place after 2 to 3 years, 93 after 4 to 5 years and 87 after 8 to 10 years17. The results of different studies were pooled for each period; these rates do not follow the same teeth over time. Most of the studies were retrospective. The rates are per tooth and do not predict the outcome for any single tooth.
The same review found four factors17 linked with the tooth staying in place. These were having a crown after treatment, having a neighbouring tooth on both sides, the tooth not serving as a bridge support, and the tooth not being a molar. The review notes that the evidence on these factors is weak.
The tooth staying in place and the tip of the root healing completely on X-rays are different things; the rate of complete healing is given above, under risks.
How is the tooth restored after root canal treatment?
A root-filled back tooth can be restored with a filling, with an onlay that covers the chewing cusps of the tooth, or with a crown. The choice depends on how much sound tooth is left.
- Teeth with a crown have been reported in observational studies17 to stay in the mouth longer.
- The only randomised trial comparing a crown with a filling covers only premolars with a carbon-fibre post (117 participants, high risk of bias) and showed no difference at 3 years18. Finding no difference does not mean the two are equivalent: according to the review, the evidence is not enough to decide18 whether a filling or a crown works better.
- A 2015 update found no study19 up to that date comparing an inlay or onlay with a crown.
So it has not been shown that every root-filled tooth needs a crown. For crowns, see the dental crowns page.
A meta-analysis pooling bonded onlays and overlays on root-filled teeth has no comparison group. In this study, failures were about 4 in every 100 restorations at 2 to 4 years, and between about 11 and 21 at 7 years or more of follow-up20. These figures are not a survival curve and do not predict the outcome for any one tooth. The authors state that most failures appeared repairable; whether repairs were done, and how they turned out, was not measured.
For front teeth, one study followed 196 direct composite veneers placed in a university clinic for an average of 3.5 years. In this retrospective study, the annual failure rate was about 5 in every 100 veneers on vital teeth and about 10 on root-filled teeth21. This does not mean a composite veneer cannot be placed on a root-filled tooth.
When to contact a dentist
Contact your dentist if any of the following happens:
- Toothache that starts on its own, wakes you at night or keeps getting worse
- A lingering ache after something hot or cold
- Pain when you bite or touch the tooth
- A pimple-like swelling or discharge on the gum
- A tooth that changes colour after a knock
- Pain or swelling that does not ease, or gets worse, after root canal treatment; a temporary filling that falls out
- Pain, swelling or discharge from the gum around a root-filled tooth, even years later
If you think you have an abscess, see a dentist without delay, even if you have no fever or swelling; a dental abscess does not go away on its own and needs urgent dental treatment5. If you have swelling in your face or jaw, or a fever, get seen the same day.
Emergencies. The following need urgent medical help5. Do not wait for a dental appointment; go to an emergency department or call 112:
- Swelling that makes it hard to breathe, speak or swallow
- Swelling that spreads to the eye or the neck
- Swelling or pain in the eye, or sudden problems with your sight
- Major swelling inside the mouth
- Difficulty opening your mouth
What determines the cost?
This page carries no prices. The treatment plan is prepared for you after an examination. The main factors that shape it are:
- The type of tooth and the number of canals (molars usually have more canals)
- The state of the canals: narrow, curved or previously filled canals
- Whether it is a first treatment or a repeat root canal treatment
- How many visits are needed
- Whether the tooth is restored afterwards with a filling, an onlay or a crown; a post, if needed
Ask for it in writing: what your plan includes, and whether the permanent restoration of the tooth (and a post, if needed) is included or charged separately.
Frequently Asked Questions
Does root canal treatment hurt?
Treatment is done under local anaesthetic. If you feel pain during the procedure, tell your dentist; more anaesthetic can be given. Some tenderness in the days after treatment is common, and it usually eases markedly within the first week.
How many visits does root canal treatment take?
Some teeth are finished in one visit; treatment often takes two or more. Studies found no clear difference in healing between treatment in one visit and treatment over several. The plan depends on the state of the tooth.
Root canal treatment, or extraction and an implant?
In studies, root-filled teeth and single crowns on implants stayed in the mouth at similar rates over the long term, but the two have rarely been compared directly. The choice depends on how much sound tooth is left, and on your gums and bone.
Do I need a crown after root canal treatment?
Not for every tooth. Observational studies report that teeth with a crown last longer; the only small trial comparing a crown with a filling showed no difference, but that does not show the two are equivalent. The decision depends on how much sound tooth is left.
What is a post, and does every tooth need one?
A post is a part placed in the root canal to hold the restoration on top when very little of the tooth is left. Not every tooth needs one; the decision depends on the remaining tooth. We do not give a source comparing teeth with and without posts on this page; ask your dentist what to expect for your tooth.
Can a root-filled tooth become inflamed again?
It can. The tip of the root does not heal fully in every tooth, and new inflammation can develop years later. If that happens, repeat root canal treatment, surgery at the tip of the root or extraction is discussed. If you notice pain, swelling or discharge from the gum, contact your dentist.
If I take antibiotics, can I avoid root canal treatment?
No. Antibiotics are not recommended for the pain of an inflamed nerve, and they do not remove the cause of an abscess. An abscess is treated by draining the pus and removing the cause; this usually means root canal treatment or an extraction.
Does a root-filled tooth turn dark?
A tooth whose nerve has died can darken over time. Such a tooth can be lightened by bleaching from the inside; your dentist will explain whether this suits your tooth and what the possible side effects are.

Dt. Dilek AKSU GÜLER
Dentist · Founder
She has completed advanced training in implantology and works in aesthetic restorations and smile design.
Sources
- Outcomes of root canal treatment and restoration, implant-supported single crowns, fixed partial dentures, and extraction without replacement: a systematic review. Journal of Prosthetic Dentistry 2007;98(4):285-311 (Torabinejad M et al.). 2007.↩doi.org
- Incidence of pulp necrosis and periapical pathosis after indirect restorations: systematic review and meta-analysis (37 studies, 11,615 teeth). BMC Oral Health 2023. 2023.↩pmc.ncbi.nlm.nih.gov
- Deep caries management: EFCD-ESE-ORCA S3-level clinical practice guideline. Caries Research 2026 (Schwendicke F et al.; co-published in Int Endod J and Clin Oral Investig). 2026.↩doi.org
- Antibiotic use for irreversible pulpitis (Cochrane review, 2019). Cochrane Database of Systematic Reviews 2019;5:CD004969. 2019.↩doi.org
- NHS: Dental abscess. NHS (nhs.uk). 2026.↩nhs.uk
- Systematic review of the survival rate and the incidence of biological, technical and aesthetic complications of single crowns on implants (46 studies, mean follow-up 5 years). Clinical Oral Implants Research 2012;23 Suppl 6:2-21. 2012.↩doi.org
- NHS: Root canal treatment. NHS. 2025.↩nhs.uk
- Single versus multiple visits for endodontic treatment of permanent teeth (Cochrane review). Cochrane Database of Systematic Reviews 2022;12:CD005296 (Mergoni G et al.). 2022.↩doi.org
- Pain prevalence and severity before, during, and after root canal treatment: a systematic review. Journal of Endodontics 2011;37(4):429-438 (Pak JG, White SN). 2011.↩doi.org
- Factors associated with endodontic flare-ups: a systematic review and meta-analysis. International Endodontic Journal 2026;59(9):1778-1791 (Ohshima J et al.). 2026.↩doi.org
- Outcome of primary root canal treatment: systematic review of the literature, part 1. International Endodontic Journal 2007;40(12):921-939 (Ng YL et al.). 2007.↩doi.org
- Oral Health Topics: Whitening. American Dental Association (ADA Library & Archives), last updated 16 August 2022. 2022.↩ada.org
- ADA evidence-based clinical practice guideline for the pharmacologic management of acute dental pain in adolescents, adults, and older adults (2024). Journal of the American Dental Association 2024;155(2):102-117. 2024.↩doi.org
- SDCEP Management of Acute Dental Problems: Analgesia (supporting tool). Scottish Dental Clinical Effectiveness Programme (SDCEP). 2026.↩acutedentalproblems.sdcep.org.uk
- Systemic antibiotics for symptomatic apical periodontitis and acute apical abscess in adults (Cochrane review, 2024). Cochrane Database of Systematic Reviews 2024;5:CD010136. 2024.↩doi.org
- SDCEP Drug Prescribing for Dentistry: Dental abscess. Scottish Dental Clinical Effectiveness Programme (SDCEP). 2026.↩sdcepdentalprescribing.nhs.scot
- Tooth survival following non-surgical root canal treatment: a systematic review of the literature. International Endodontic Journal 2010;43(3):171-189 (Ng YL, Mann V, Gulabivala K). 2010.↩doi.org
- Single crowns versus conventional fillings for the restoration of root filled teeth (Cochrane review). Cochrane Database of Systematic Reviews 2012;(5):CD009109 (Fedorowicz Z et al.). 2012.↩doi.org
- Single crowns versus conventional fillings for the restoration of root-filled teeth (2015 update). Cochrane Database Syst Rev 2015;(9):CD009109. 2015.↩doi.org
- The influence of indirect bonded restorations on clinical prognosis of endodontically treated teeth: a systematic review and meta-analysis. Dent Mater 2022;38(8):e203-e219. 2022.↩doi.org
- Direct anterior composite veneers in vital and non-vital teeth: a retrospective clinical evaluation. J Dent 2015;43(11):1330-6. 2015.↩doi.org