
What is a Hollywood smile?
A "Hollywood smile" usually means veneers or crowns on the front teeth that show when you smile, often in a very white, even shade. Veneers are thin shells on the front of a tooth; crowns cover the whole tooth. It is a request for a look, not a treatment. A good plan looks for the option that meets your aim with the least loss of tooth tissue.
On healthy teeth, preparing for veneers or crowns usually removes tissue that does not grow back, and each prepared tooth then depends on a restoration. Depending on your teeth, the plan may instead be whitening, bonding, orthodontics or gum reshaping, veneers or crowns on only some teeth, or no treatment. Deciding which, and in what order, is called smile design. This page explains how such a plan is made, what each option removes from the tooth and how to judge it.
- On healthy teeth, preparing for veneers or crowns cannot be undone, and every prepared tooth then needs a restoration.
- Whitening, bonding and orthodontics are considered first; the plan may end with them alone, or with no treatment.
- The shade cannot be changed once a veneer or crown is bonded. Agree on it first, after any whitening of your own teeth.
- In suitable cases, a trial (mock-up) shows the planned shape in your mouth before any tooth is prepared, but not the exact result.
Who it suits, and who it does not
Where veneers or crowns on several front teeth may be suitable
- Discolouration on several front teeth that whitening does not correct
- Worn, chipped or misshapen front teeth (for worn teeth, the cause, such as clenching, grinding or acidic food and drink, is assessed first)
- Old fillings and crowns that no longer match
- Healthy gums, no active decay and, for veneers, enough enamel on the teeth
Where another treatment is needed first
- Active decay or gum disease. These are treated first.
- Uncontrolled clenching and grinding. This increases the risk of ceramics breaking. It is assessed first and protection such as a night guard is agreed; for some people, veneers may not be suitable.
- Marked misalignment. Orthodontics is assessed first; covering it with veneers or crowns removes a lot of tissue from the teeth.
Who it is not for
- Sound, straight teeth when the only wish is a whiter colour. Whitening is considered first, because it does not cut the tooth. It does not reach the same shade on every kind of discolouration. The plan may end with whitening alone.
- Teeth that are still developing. In young patients, veneers and crowns are usually postponed.
- Pregnancy and breastfeeding. Cosmetic procedures that are not essential, whitening in particular, are usually postponed until after this period.
- Expectations that do not match the condition of the teeth. Where a trial is possible, it gives an idea of the look that can be reached. The plan is then discussed again on that basis.
A good plan gives a reason for each tooth. A single-line offer such as "veneers on all the front teeth" should be explained tooth by tooth if it includes sound teeth.
Options, from the least tissue removed to the most
The list below runs roughly from the options that remove the least tooth tissue to those that remove the most. Orthodontics and gum reshaping do not fit neatly on this scale, because some plans involve an extraction or surgery on the gum and bone. It is not a ladder: each treatment answers a different problem, and not all of them need to be done.
- Doing nothing, or waiting. If your teeth and gums are healthy, leaving them as they are is a valid choice. Nothing is removed, and you can decide later.
- Whitening. It is considered for a colour concern, once the cause of the discolouration has been assessed. It can cause temporary sensitivity and gum irritation. It does not lighten existing fillings, crowns or veneers1. It does not give the same result on every kind of discolouration. Yellowish teeth usually respond well, brownish teeth may respond less, and greyish teeth may not lighten at all. The effect fades: the teeth partly return to their earlier colour over time, and the treatment can be repeated. If you want your own teeth lighter, whitening comes first, so that the shade of any veneer, crown or bonding can be matched to them. After whitening, time is allowed for the colour to settle and for conditions to suit bonding; your dentist decides how long.
- Bonding (adding tooth-coloured composite to the tooth). For small chips, worn edges, small gaps and reshaping a single tooth. The tooth is usually not cut, but its surface is treated so that the material bonds. Composite is easier to repair than ceramic, but stains and wears more easily2.
- Orthodontics. For crowding, rotated teeth and gaps. It moves the teeth into line instead of reducing them for veneers or crowns, takes months, often years, and needs retention afterwards. Some plans need limited reshaping of the enamel between the teeth, or an extraction. The risks of shortening of the root tips, white spots on the enamel and gum recession are assessed separately. "Correcting" crowded teeth with veneers or crowns means removing a great deal of tissue from the teeth.
- Gum reshaping. When too much gum shows, the cause is assessed first. It may lie in the gum level, the position of the supporting bone or of the teeth, the jaw structure or how the lip moves. In suitable cases, the gum, and the supporting bone where needed, is reshaped surgically. In others, orthodontics or different treatments are considered. Possible sensitivity, exposure of the root surface and changes in the appearance over time are discussed in advance.
- Laminate veneers. For changing the colour and shape of several front teeth together, when there is enough enamel. Enamel is usually removed, and removed enamel does not grow back, so the treatment cannot be undone2.
- Crowns. Whether a crown is needed depends on the sound tissue left, any cracks and the chewing load. A root canal treatment or a large filling does not on its own mean a crown is needed. Options that remove less tissue, such as fillings and onlays (restorations that cover part of the chewing surface), are considered first. Where too little sound tissue is left, a crown may be the right choice. On a sound tooth, a crown only for appearance is not the first option: it removes far more tissue than a veneer or bonding.
The comparison table that sets these options side by side is on the dental veneers and crowns page.
Choosing the colour: very white or close to your own?
Many people who ask for a Hollywood smile picture a very white, even row of teeth. That is one possible choice, not a clinical standard. The shade, shape and size of the new teeth are agreed before anything is made, after any whitening of your own teeth.
- The colour is fixed once bonded. The colour of a veneer cannot be changed after it has been bonded3, and whitening does not lighten ceramic.
- Teeth that are not covered can change colour. Unlike ceramic, natural teeth can change colour over time, so a difference can appear between them and the restorations. This applies to the back teeth, and to the lower teeth if only the upper ones are treated.
- Shape and size are a choice too. Where a trial (mock-up) is possible, you can see the planned shape in your mouth before any tooth is prepared. The final colour and translucency of the ceramic can look different from the trial.
If you are unsure, ask to see the planned shade next to your own teeth before you agree.
How smile design works, step by step
Smile design is the planning that decides which treatments, in which order, can reach the look you want. The steps can vary between clinics. Where a trial is possible, the order below lets you try the planned look before any tooth is prepared. It also helps you choose the route that removes the least tooth tissue.
Defining the concern
What you want to change is made specific: colour, shape, alignment, how much gum shows, gaps. Each concern has a different solution. Trying to solve them all with one procedure often means choosing the route that removes the most tooth tissue.
Examination and records
The health of the teeth and gums, the bite and any clenching or grinding habit are assessed. Your medical history and medicines are reviewed too. Photographs, an intraoral scan or impressions, and X-rays if needed, are taken. Active decay and gum disease are treated first.
Digital design
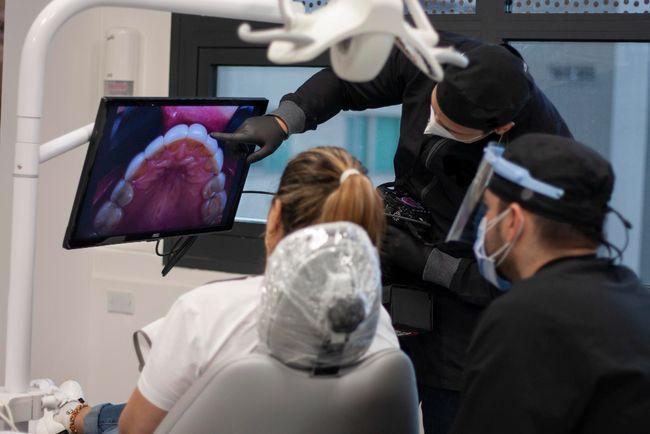
The length and width of the teeth and their relation to the lips are planned on the photographs and the scan. This is a visualisation, not a promise; the result depends on the actual condition of the teeth.
Trial (mock-up)
In suitable cases, the design is applied to your teeth in a temporary material, usually without cutting the teeth. On crowded or protruding teeth, a trial made by adding material can make the teeth look bulkier than they will be. It cannot represent every plan, and your dentist tells you this in advance. The trial gives an idea of the approximate shape and look; the final colour, translucency and gum appearance may differ. You can test the look, your speech and your bite, and ask for changes.
Setting the treatment order
Which procedure goes on which tooth is written down tooth by tooth. Health problems come first, then procedures that usually do not cut the tooth, such as whitening and orthodontics. Bonding, veneers and crowns are not steps that follow one another. They are alternatives chosen according to the condition of each tooth, and are used only on the teeth that need them.
Treatment and review
The treatments are carried out in the planned order. For veneers and crowns, the teeth are usually prepared under local anaesthetic and the restorations made in a laboratory, with a try-in before bonding. Temporary restorations may be worn in between. After the final restorations are bonded, the bite is adjusted. At the review appointment, how the gums have settled and any sensitivity are assessed.
Risks and benefits
Risks
A Hollywood smile plan may treat many healthy teeth at once. Each prepared tooth carries the risks below, so the more teeth are prepared, the more teeth are exposed to them. The figures come from published studies, not from our own records.
- Tissue that does not grow back. For a veneer, a layer of enamel is usually removed from the front of the tooth. For a full crown, enamel is removed from every surface, and often the dentine beneath it. The tissue removed does not grow back2; the tooth depends on a restoration for life.
- Going beyond the enamel. The more a tooth is reduced, for example to cover crowded teeth, the more dentine is exposed. A retrospective study followed 672 veneers for up to 15 years, about 6 on average. Failure was seen more often where dentine had been exposed4 than where the preparation stayed within the enamel.
- Sensitivity. Teeth can become more sensitive because some enamel is removed3.
- The nerve of the tooth. Teeth that were alive at the start and then receive indirect restorations, such as crowns, partial crowns or bridges, can lose their vitality. In the pooled result of 37 studies with different follow-up periods, this was seen in about 5 in every 100 teeth5. The certainty of the evidence is low. The figure is not your personal risk, and it is not a yearly rate. The more crowns there are, the more likely it is that at least one tooth is affected. If the nerve dies, root canal treatment is needed to keep the tooth; the figure above is not a root canal treatment rate.
- Fracture and debonding. These are the main reasons ceramic veneers fail6; clenching and grinding increase the risk.
- Colour mismatch. Ceramic keeps the colour it was made in, while natural teeth can change over time; a difference can appear.
- Decay and gums. A crown or veneer does not protect the tooth from decay. New decay and gum inflammation can develop at the edge of restorations that do not fit well or are not cleaned well enough. The gum can also recede. In a review of studies on crowns, inlays and onlays, decay was the main biological complication7.
- Repair and replacement. Restorations do not last for life; over time they may need repair or replacement, which has an additional cost. The more teeth are treated, the greater this burden becomes.
- Expectations. A digital design is a visualisation; the real result depends on the condition of the teeth, the gums and the bite. Images presented as a promise are misleading.
Benefits
- Veneers and crowns can change the colour, shape and size of several teeth together, where whitening or bonding cannot reach the aim.
- Planning treatment for all your concerns together, rather than one at a time, aims to avoid unnecessary or conflicting procedures.
- Where a trial is possible, it lets you assess the planned look before any tooth is prepared, and change your mind.
- A plan done in the right order can end with the option that removes the least tooth tissue, on fewer teeth.
After treatment, and daily care
Care depends on the treatment carried out; the shared principles are:
- After teeth are prepared, they can be more sensitive to hot and cold. Sensitivity that lasts more than a week or keeps getting worse is a reason to contact your dentist.
- Brush twice a day with a fluoride toothpaste. Clean the edges of restorations and between your teeth every day.
- Do not bite your nails, pens or hard objects with your front teeth. If you clench or grind, a night guard may be recommended.
- The colour of whitened teeth partly returns over time. Whitening does not change the colour of ceramic. Ceramic stains less than bonding composite, although discolouration can appear along its edges over time. Colour differences between restorations and your natural teeth are assessed at check-ups.
- If you have had orthodontics, wear the retainer for as long as your dentist recommends; without it, teeth tend to move back.
- Come for regular check-ups; the edges of restorations, the gums and the bite are assessed.
How long does the result last?
How long any result will last cannot be known for certain in advance. The figures below come from published studies, not from our own records.
The effect of whitening fades over time8, and the teeth partly return to their earlier colour.
A 2025 review combined 29 studies of ceramic veneers. About 94 to 97 in every 100 veneers were still in place9 after an average follow-up of about 10 years. The range covers feldspathic, leucite-reinforced and lithium disilicate ceramics; there are no long-term data for zirconia veneers.
The great majority of single crowns on natural teeth are still in place after five years10, according to a 2026 review of 64 studies.
A restoration that is still in place is not necessarily free of complications. It may have needed repair, and in time it may need replacing. The result depends on the condition of the teeth, the bite, your habits and your care.
How to judge a Hollywood smile plan
- What is proposed for which tooth, and why? Ask for a reason for each tooth.
- Is doing nothing, or waiting, also an option? For healthy teeth, the consequences of not treating and of postponing should be discussed too.
- Why is a less invasive option not enough for this tooth? The answer should rest on the condition of the tooth, not on a one-size-fits-all offer, the material or a deadline.
- Veneer or crown, and why? A veneer covers the front surface of a tooth; a crown covers the whole tooth2. If a crown is proposed for a healthy front tooth, ask why a veneer or bonding is not enough.
- Is there a trial stage? Can you try the planned look in your mouth before any tooth is prepared?
- How much tissue will be removed, and from how many teeth? This is decided by a clinical examination and restorative planning; X-rays are used when clinically needed. A plan made from photographs alone is only a preliminary assessment, not a firm plan.
- Could a root canal treatment be needed? For teeth where crowns are planned, the condition of the nerve is assessed in advance.
- How long, and how many appointments? Ask how many appointments the plan needs and over what period, including the try-ins and the review.
- What happens afterwards? Ask in writing who will deal with a fracture, a debonded restoration or sensitivity, and how.
If you are undecided between two plans, getting a second opinion is normal; ask for your photographs and X-rays. You can say no, or take time to decide, before any tooth is prepared.

When to contact a dentist
Contact your dentist if any of the following happens after treatment:
- Sensitivity that lasts more than a week or keeps getting worse
- Pain when biting, or a feeling that the bite is too high
- A break, crack or movement in a restoration; a crown or veneer coming off (keep the piece)
- Bleeding, recession or a dark line in the gum at the edge of a restoration
Emergencies. Throbbing pain, facial swelling or a fever are not an expected result; see a dentist without waiting. Some signs need emergency care: difficulty breathing or swallowing, swelling in the mouth and neck that spreads quickly, or swelling around the eye. In that case, go to an emergency department or call 112.
What determines the cost?
Fees are not given on this page. The main factors that affect the cost are:
- Which treatments it includes
- How many teeth are treated
- The material and how it is made
- Treatment needed first: decay, gums, root canal treatment
- The trial and review appointments
For comparable treatments, the fewer teeth are treated, the lower the cost and the fewer teeth lose tissue. Ask for the plan in writing, showing which procedure is proposed for which tooth, and why.
Ask for a plan for your smile
Send a photograph of yourself smiling and tell us what you would like to change. Our dentists will set out the options tooth by tooth, starting from the one that removes the least tooth tissue. A view from a photograph is preliminary; the examination confirms or changes it.


Frequently Asked Questions
Is a Hollywood smile the same as smile design?
Not quite. Smile design is the planning: the teeth, gums, lips and face are assessed together, and the treatments and their order are decided. A Hollywood smile is the look many people ask for, usually veneers or crowns on the front teeth that show when they smile. A smile design plan may end with veneers or crowns, with less invasive treatment such as whitening, bonding or orthodontics, or with no treatment.
Will a Hollywood smile damage my teeth?
Veneers and crowns usually mean removing tooth tissue, and removed enamel does not grow back. For a veneer, a layer of enamel is usually removed from the front of the tooth. For a crown, the tooth is reduced on every side, often into the dentine. On healthy teeth this cannot be undone. Each prepared tooth will need a restoration from then on, and restorations may need repair or replacement over time. The nerve of a tooth can die after it is crowned, and root canal treatment is then needed to keep the tooth. This is why a good plan starts from the options that remove the least tissue and treats only the teeth that need it.
Can I get the look without veneers?
It depends on what you want to change. Whitening lightens your natural teeth without cutting them, although it does not work equally well on every kind of discolouration. Bonding, tooth-coloured composite added to the tooth, can close small gaps and repair chips or worn edges, usually without cutting the tooth. Orthodontics straightens crowded or rotated teeth by moving them rather than making them smaller. Some plans need limited reshaping of the enamel between the teeth. Gum reshaping may help when a lot of gum shows. A plan may end with one or more of these and no veneers at all.
Does it hurt?
It depends on the treatment. Whitening can cause temporary sensitivity and gum irritation. Teeth are usually prepared for veneers or crowns under local anaesthetic. Afterwards, the teeth can be more sensitive, because enamel has been removed. Sensitivity that lasts more than a week or keeps getting worse, or pain that wakes you at night, is not expected; contact your dentist.
How long does a Hollywood smile take?
It depends on the plan. Whitening in the clinic and bonding are quick. Veneers and crowns usually need more than one appointment, with laboratory work and try-ins in between. Orthodontics takes months, often years; if veneers or crowns are still needed, they come afterwards. Ask how many appointments the plan needs and over what period, including the try-ins and the review.
Is a Hollywood smile permanent?
Preparing teeth for veneers or crowns cannot be undone. The tooth tissue removed does not grow back, so you cannot go back to your old teeth. How long the veneers or crowns themselves will last cannot be known for certain in advance. The figures from studies are given on this page, under "How long does the result last?". A restoration that is still in place is not necessarily free of complications. It may have needed repair, and in time it may need replacing. Whitening fades over time. The result depends on the condition of the teeth, the bite, your habits and your care.
I was offered veneers or crowns on all my front teeth. Is that right?
When the same procedure is proposed for all the front teeth, there should be a reason for each tooth. Ask why whitening, bonding or orthodontics is not enough for each one, and why a crown rather than a veneer where a crown is proposed. Getting a second opinion is normal. You can say no, or take time to decide, before any tooth is prepared.

Dt. Dilek AKSU GÜLER
Dentist · Founder
She has completed advanced training in implantology and works in aesthetic restorations and smile design.
Sources
- Teeth Whitening (patient information). American Dental Association, MouthHealthy.↩mouthhealthy.org
- Veneers. American Dental Association, MouthHealthy.↩mouthhealthy.org
- Veneers. healthdirect Australia (government-funded health information), last reviewed February 2025. 2025.↩healthdirect.gov.au
- Ceramic veneers and dentin exposure: 672 veneers in 189 patients, 1-15 years (mean 6 years). Journal of Esthetic and Restorative Dentistry 2025. 2025.↩pmc.ncbi.nlm.nih.gov
- Incidence of pulp necrosis and periapical pathosis after indirect restorations: systematic review and meta-analysis (37 studies, 11,615 teeth). BMC Oral Health 2023. 2023.↩pmc.ncbi.nlm.nih.gov
- Survival and failure causes of ceramic laminate veneers: systematic review (25 studies, 6,500 veneers, 3-21 years). Journal of Clinical Medicine 2021;10(5):1074. 2021.↩pmc.ncbi.nlm.nih.gov
- Complications and survival rates of inlays and onlays vs complete coverage restorations: a systematic review and analysis of studies. J Oral Rehabil 2018;45(11):903-920. 2018.↩doi.org
- Tooth bleaching: umbrella review of 28 systematic reviews (416 randomised trials). Heliyon 2024. 2024.↩pmc.ncbi.nlm.nih.gov
- Survival and complication rates of ceramic laminate veneers by material: systematic review and meta-analysis (29 studies). Journal of Esthetic and Restorative Dentistry 2025;37(3):601-619. 2025.↩doi.org
- Survival of monolithic lithium disilicate, monolithic zirconia and metal-ceramic single crowns: systematic review. International Journal of Prosthodontics 2026;39(3):308-324. 2026.↩doi.org
Specialists Who Perform This Treatment

Dt. Alp Tolga ÇİNTAV
Postgraduate training in dentomaxillofacial radiology.
Dt. Dilek AKSU GÜLER
She has completed advanced training in implantology and works in aesthetic restorations and smile design.

Dt. Furkan ALTINEL
Dentist; aesthetic dentistry, implants and prosthetic treatments

Dt. Furkan YAĞCIOĞLU
Dentist; smile design and All-on-4 / All-on-6 implant-supported prostheses

Dt. Hakan AKMAN
Specialty training at the Department of Oral and Maxillofacial Surgery, Ankara University (1996-2003).

Uzm. Dt. İsmail KILIÇ
Prosthodontics Specialist; aesthetic dentistry, digital smile design and implants

Uzm. Dt. Uğur AĞAR
Orthodontics Specialist; braces, clear aligners and smile design